
Why researchers are paying close attention to one of the most intriguing investigational obesity combinations currently under development.
Original report: July 2026. Latest clinical development update: November 6, 2026.
November 6, 2026 Update: EloraTZP Phase 3 AMPLIFY-2 Is Recruiting
Eli Lilly’s investigational eloralintide–tirzepatide coformulation, known as EloraTZP and identified as LY900043, has reached a documented Phase 3 development milestone. The AMPLIFY-2 registry record (NCT07881458), updated November 4, 2026, now lists the study as Recruiting. Lilly’s official AMPLIFY-2 page independently describes it as enrolling. The registry gives October 16, 2026 as the actual study start, superseding an earlier estimated November start.
Phase 3 registry snapshot | verified November 6, 2026
Important: Trial recruiting status is a study milestone, not a clinical result or evidence of approval.
What changed, and what did not?
The meaningful news is the transition from a registered, not-yet-recruiting protocol to an active recruiting study. This is not the same as a positive trial result. Recruiting does not reveal how many participants have enrolled, whether the first participant has received study drug, or how effective the coformulation will be. No AMPLIFY-2 efficacy or safety outcomes have been posted. EloraTZP remains investigational, with no regulatory approval established by this milestone.
How AMPLIFY-2 is designed
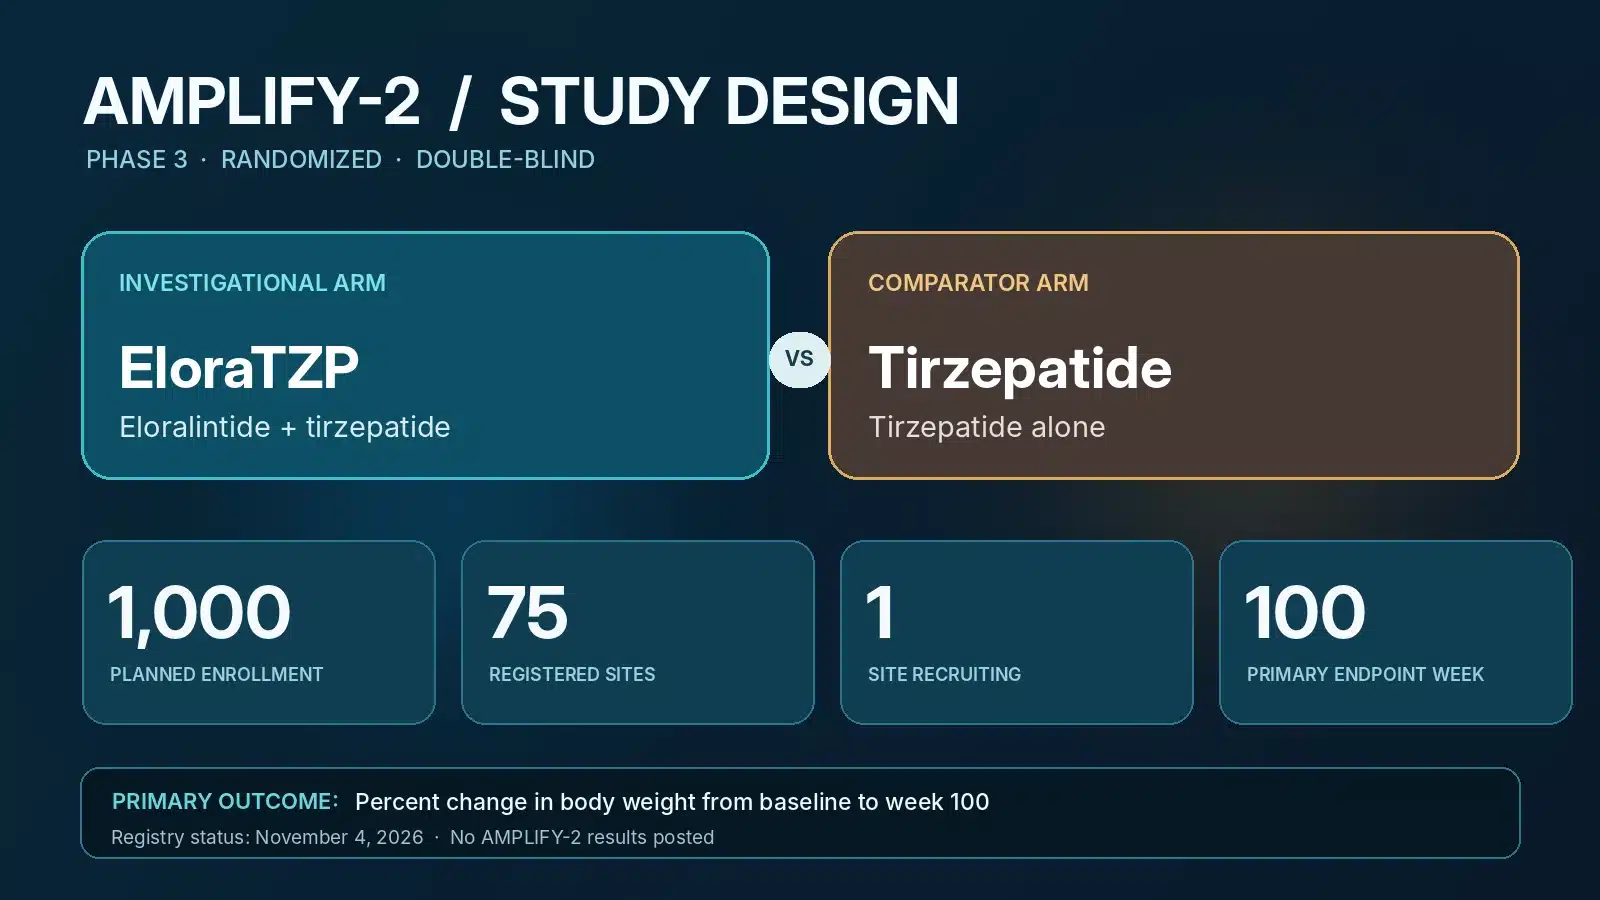
AMPLIFY-2 is a multicenter, randomized, double-blind, parallel-group Phase 3 comparison of EloraTZP versus tirzepatide alone. The trial targets approximately 1,000 adults with obesity or overweight and type 2 diabetes. The eligibility criteria include a body mass index of at least 27, and the protocol uses a defined set of metabolic and other screening criteria. Lilly describes weekly investigational treatment; the trial records describe subcutaneous administration. The specific dose strengths and escalation schedule are not established by the public summary reviewed here, so earlier research doses should not be presented as this Phase 3 protocol.
The primary outcome is percentage change in body weight from baseline at week 100. Additional measures include cardiometabolic and body-composition endpoints, such as HbA1c, waist circumference and total body fat mass, along with safety and tolerability assessment. That longer observation period matters because a stronger early weight-change signal is only one question; sustained effects and adverse-event patterns can materially change a research program’s interpretation.
Seventy-five locations does not mean seventy-five are enrolling
The November 4 registry snapshot lists 75 research locations internationally. Only one location, the Los Angeles Institute for Metabolic Research, was marked as recruiting in the site-level data reviewed November 6; the remaining locations were listed as not yet recruiting. Site-level status may change. An overall trial status of Recruiting therefore should not be mistaken for all registered centers being open or for confirmation that the full enrollment target has been met.
AMPLIFY-1 is a different trial
Lilly has also registered AMPLIFY-1 (NCT07881432), a separate Phase 3 trial in adults with obesity without type 2 diabetes. That study plans approximately 2,115 participants and includes EloraTZP, eloralintide alone, tirzepatide alone and placebo comparison groups. As of November 6, AMPLIFY-1 remains Not Yet Recruiting, with a December 2026 estimated start. Its population and comparison groups differ from AMPLIFY-2, so the two trials must not be collapsed into a single study.
Where the earlier 48-week Phase 2b findings fit
This article’s earlier update summarizes Lilly’s reported 48-week Phase 2b combination results. Those results provide context for why a larger Phase 3 program was initiated; they are not results from AMPLIFY-2. The new protocol asks whether a coformulation can demonstrate an interpretable longer-term benefit relative to tirzepatide alone while measuring tolerability. Neither the historical Phase 2b percentage nor an earlier dose-escalation approach should be projected onto the new trial as a guaranteed outcome.
Timeline and what researchers should watch
- October 16, 2026: actual AMPLIFY-2 study start recorded.
- November 4, 2026: recruitment-status update posted to the registry.
- October 2029: estimated primary completion, subject to change.
- November 2029: estimated overall study completion, not necessarily the publication date for results.
The next useful checkpoints are additional sites opening recruitment, subsequent registry updates, completion of enrollment, conference presentations and eventual analyzed findings. The scientific question is still open: will amylin-receptor activation combined with dual incretin activity offer a durable benefit that justifies its safety and tolerability profile? Trial activation alone cannot answer that.
For additional research context: See Xcel’s eloralintide research guide and separate preclinical ADA report. For independently maintained, trial-specific references, consult the PeptideBlog AMPLIFY-2 tracker, Eloralintide Research trial record, the Weight Loss Atlas eloralintide overview, and the Atlas November 6 AMPLIFY-2 recruiting update. The official registry record and Lilly trial listing remain the primary sources for the AMPLIFY-2 development status.
Scientific and regulatory note: This update reports clinical-trial research involving investigational medicines. It does not imply approval or establish suitability of research-only chemical reference materials for human or veterinary use. Research materials are not sterile and are not for injection.
Research update: Lilly presented Phase 1 and Phase 2b data after this article was first published. In a 48-week Phase 2b trial involving 367 adults with obesity or overweight and type 2 diabetes, the Lilly trial report described mean weight reductions from baseline of 23.3% in the highest studied combination group, 14.8% in the tirzepatide-only comparator and 3.0% with placebo, using the efficacy estimand. The primary endpoint compared the combination with placebo; comparisons with the individual compounds were secondary. Gastrointestinal events were more frequent in the combination groups than with either compound alone. Lilly reported adverse-event discontinuation rates of 10.8% to 27.0% across combination groups, compared with 2.9% for tirzepatide alone and 16.7% for placebo. These are group-level clinical trial results, and the study does not establish approval, long-term safety or a use for laboratory reference materials. See the Eloralintide Research analysis of the Phase 2b report for additional study context.
Phase 3 program: The registered AMPLIFY-1 study compares the eloralintide–tirzepatide coformulation with its individual components and placebo in adults with obesity without diabetes. AMPLIFY-2 compares the coformulation with tirzepatide in adults with overweight or obesity and type 2 diabetes. The registrations describe study plans, not results. For trial-by-trial context, see the independent clinical development overview.
A New Conversation Is Beginning
Obesity research rarely stands still.
Over the last decade, the field has experienced one of the fastest periods of innovation in pharmaceutical history. Obesity treatments have evolved, and several medications have produced substantial average weight reductions in clinical studies. Results vary across treatments and populations; separate trials do not establish equivalence to bariatric surgery.
Semaglutide changed expectations.
Tirzepatide raised them again.
Retatrutide expanded the conversation even further.
Now another investigational compound has quietly begun attracting increasing attention among clinicians, researchers, investors, and obesity specialists.
Its name is Eloralintide.
Unlike many recent obesity therapies, Eloralintide is not simply another incretin drug attempting to outperform today’s market leaders. Instead, it represents Lilly’s continued investment in selective amylin receptor biology, a pathway many researchers believe could become an important component of future obesity treatment strategies.
Early Phase 1 research evaluated eloralintide alongside tirzepatide. Lilly subsequently presented additional data, including 16-week results and the separate Phase 2b trial described above.
The real story may not be one reported percentage.
The real story is where obesity research appears to be heading.
The Evolution of Obesity Medicine
To understand why Eloralintide has generated so much interest, it’s important to understand how obesity pharmacology has evolved.
First Generation: GLP-1 Changed Everything
When GLP-1 receptor agonists entered clinical practice, they fundamentally changed expectations surrounding pharmacologic weight management.
These medications demonstrated that appetite regulation could be influenced through hormonal signaling rather than relying solely on willpower, calorie restriction, or surgical intervention.
For the first time, physicians began observing sustained double-digit weight reduction with medication alone.
The field changed almost overnight.
Second Generation: Dual Incretin Biology
Lilly’s development of Tirzepatide represented another major scientific leap.
Instead of targeting only GLP-1 receptors, researchers combined GLP-1 and GIP receptor agonism into a single molecule.
The result wasn’t simply another obesity medication.
It showed that a compound engaging two receptors could be studied against a single-receptor comparator. Results depend on the compounds and trials involved, so receptor count alone does not establish superiority.
That finding changed how researchers began thinking about obesity pharmacology.
Third Generation: Expanding Beyond Dual Agonists
Retatrutide introduced yet another concept.
Rather than relying solely on GLP-1 and GIP, investigators added glucagon receptor activity.
Each additional pathway contributed another layer of metabolic regulation.
By this point, the scientific conversation had shifted dramatically.
Instead of asking how to make one pathway stronger, researchers increasingly focused on how multiple biological systems might work together.
That philosophy continues today.
Enter Eloralintide
This is where Eloralintide becomes particularly interesting.
Unlike Semaglutide.
Unlike Tirzepatide.
Unlike Retatrutide.
Eloralintide is not another incretin molecule.
Instead, Lilly designed it around selective amylin receptor agonism.
That distinction matters.
Rather than competing directly with GLP biology, Eloralintide explores an entirely different hormonal system involved in regulating appetite, satiety, meal size, gastric emptying, and energy balance.
In other words…
Researchers aren’t simply asking,
“Can we make a stronger GLP?”
They’re asking,
“What happens when entirely different biological systems work together?”
That represents an important strategic shift.
Understanding Amylin Biology
Amylin is a naturally occurring peptide hormone secreted alongside insulin by pancreatic beta cells following food intake.
Although insulin receives most of the attention, amylin performs several equally important physiological functions.
Current research suggests amylin contributes to:
- Meal termination
- Satiety signaling
- Gastric emptying
- Post-meal glucagon suppression
- Central appetite regulation
- Energy balance
Unlike incretins, amylin communicates with specialized receptor complexes distributed throughout regions of the brain involved in appetite regulation.
These receptor systems include calcitonin receptors associated with receptor activity-modifying proteins (RAMPs), creating pharmacological characteristics distinct from GLP-1 receptor signaling.
Because these pathways differ biologically, many researchers believe they may complement rather than compete with incretin therapies.
Why Lilly’s Strategy Is So Interesting
One of the most fascinating aspects of Lilly’s obesity pipeline isn’t any individual molecule.
It’s the strategy itself.
Rather than focusing on a single therapeutic platform, Lilly has continued expanding across multiple mechanisms simultaneously.
Their metabolic pipeline includes:
- GLP biology
- Dual incretin agonists
- Triple agonists
- Selective amylin agonists
- Combination research programs
- Additional investigational metabolic therapies
Viewed collectively, this resembles a long-term platform strategy rather than development of one standalone blockbuster drug.
That broader perspective helps explain why compounds like Eloralintide continue attracting scientific interest.
Recent Discussions Surrounding Combination Research
Lilly later presented Phase 1 study details on eloralintide combined with tirzepatide. The groups and timepoints below describe early research, not dosing guidance or a recommended regimen.
According to those reports, investigators evaluated multiple dose combinations while exploring different titration strategies.
The reported treatment arms discussed include:
| Reported Combination | Reported Timepoint |
|---|---|
| Eloralintide 3 mg + Tirzepatide 5 mg | 16 weeks |
| Eloralintide 6 mg + Tirzepatide 5 mg | 16 weeks |
| Eloralintide 9 mg + Tirzepatide 5 mg | 16 weeks |
| Eloralintide titrated to 9 mg + Tirzepatide titrated to 15 mg | 31 weeks (reported assessment) |
Based on the reporting currently being discussed, these treatment groups were associated with substantial body-weight reductions that generated considerable attention across obesity-focused scientific discussions.
Study populations, titration schedules and timepoints differ, so these results should not be treated as interchangeable with the separate 48-week Phase 2b study. The broader research question remains:
Can selective amylin agonism meaningfully complement incretin therapy?
That question is considerably larger than one dataset.
Why Researchers Find Combination Biology So Compelling
Human metabolism isn’t regulated by one hormone.
It never has been.
Body weight represents the combined influence of dozens of interacting physiological systems including:
- Appetite regulation
- Meal termination
- Satiety
- Energy expenditure
- Gastric emptying
- Nutrient sensing
- Neuroendocrine signaling
- Reward pathways
Modern obesity pharmacology increasingly reflects that complexity.
Rather than continually maximizing one pathway, researchers appear increasingly interested in activating complementary biological systems that regulate different aspects of energy balance.
Viewed through that lens, Eloralintide becomes far more than “another obesity drug.”
It represents another piece of an increasingly sophisticated biological puzzle.
Beyond Weight Loss Alone
One lesson emerging throughout obesity research is that efficacy represents only one component of successful therapy.
Researchers are increasingly interested in understanding:
- Long-term durability
- Lean body mass preservation
- Cardiometabolic improvements
- Glycemic outcomes
- Treatment adherence
- Gastrointestinal tolerability
- Dose optimization
- Maintenance strategies
These questions often determine the long-term clinical impact of investigational therapies.
Future studies involving Eloralintide will likely continue exploring many of these endpoints.
Why Eloralintide Continues To Stand Out
Among the growing number of investigational metabolic therapies currently under development, Eloralintide occupies a unique position.
Rather than extending incretin biology, it expands obesity pharmacology into selective amylin receptor biology.
That distinction alone makes it scientifically important.
Whether evaluated as a standalone therapy or as part of broader combination strategies, Eloralintide represents one of several next-generation approaches attempting to improve our understanding of appetite regulation and metabolic disease.
For researchers following obesity science closely, that alone makes it a program worth watching.
Final Thoughts
Obesity medicine is entering an entirely new era, and the pace of innovation shows no signs of slowing down. What began with GLP-1 receptor agonists has evolved into dual agonists, then triple agonists, and now researchers are increasingly exploring how complementary biological pathways might work together rather than relying on a single mechanism alone.
That shift may ultimately prove to be one of the most important developments in metabolic medicine. Instead of searching for one “perfect” molecule, scientists are building a more complete understanding of the complex hormonal networks that regulate appetite, satiety, energy balance, and body weight. As that understanding grows, therapies designed to target multiple pathways intelligently could redefine what is possible in obesity treatment.
Recent discussions surrounding Eloralintide have renewed interest in exactly that possibility. While many scientific questions remain unanswered, the compound has emerged as one of the more intriguing investigational therapies currently under development—not simply because of the attention surrounding recent reports, but because of the unique biology it brings to the conversation.
Whether Eloralintide ultimately becomes a standalone therapy, an important combination partner, or something else entirely remains to be seen. That’s precisely why the coming years of research will be so closely watched.
One thing, however, appears increasingly clear: the future of obesity therapeutics is unlikely to be defined by a single breakthrough drug. Instead, it will almost certainly be shaped by a deeper understanding of how multiple biological systems interact—and how researchers can leverage those interactions to develop more effective, more durable treatments for obesity and metabolic disease.
As new clinical data, conference presentations, and peer-reviewed publications become available, we’ll continue updating this article to provide the latest developments surrounding Eloralintide and the rapidly evolving science of next-generation obesity therapeutics.
Frequently Asked Questions (FAQ)
What is Eloralintide?
Eloralintide is an investigational peptide therapy being developed by Lilly for the treatment of obesity and related metabolic conditions. Unlike GLP-1 receptor agonists such as semaglutide or dual incretin therapies like tirzepatide, Eloralintide is designed as a selective amylin receptor agonist, targeting a different hormonal pathway involved in appetite regulation, satiety, and gastric emptying.
Is Eloralintide a GLP-1 drug?
No. Eloralintide is not a GLP-1 receptor agonist. Instead, it targets the amylin signaling system, which plays a complementary role in regulating hunger, meal size, and feelings of fullness. Because it works through a different biological mechanism, researchers are exploring how it may fit alongside incretin-based therapies rather than directly replacing them.
How does Eloralintide differ from Tirzepatide?
Although both compounds are being studied for obesity, they work through different biological pathways.
Tirzepatide activates both the GLP-1 and GIP receptors, influencing glucose regulation and appetite through incretin biology. Eloralintide, by contrast, selectively targets amylin receptors, which are involved in satiety signaling and meal termination.
Because these mechanisms are different, researchers are interested in understanding whether they may work together in complementary ways.
Why are researchers interested in amylin biology?
Amylin is a naturally occurring hormone released alongside insulin after meals. It helps regulate appetite, slows gastric emptying, reduces food intake, and contributes to feelings of fullness.
As obesity research has evolved, scientists have increasingly explored therapies that activate multiple hormonal systems simultaneously. Selective amylin receptor agonists represent one of the most promising areas currently under investigation because they target biological pathways that differ from traditional incretin therapies.
Why has Eloralintide received so much attention recently?
Interest grew as Phase 1 and Phase 2b studies examined eloralintide with tirzepatide. See the dated update and developer sources above for the separate study designs and results.
While additional scientific information is expected as more conference materials and publications become available, the discussions have highlighted growing interest in combination approaches that leverage complementary biological mechanisms.
What do the recent reports suggest?
Lilly reported separate Phase 1 and 48-week Phase 2b studies of eloralintide with tirzepatide. The Phase 2b study enrolled adults with overweight or obesity and type 2 diabetes.
The studies investigate whether the pathways may complement one another. They have different designs and populations; the findings do not establish approval, long-term safety or an appropriate use for research materials. For the earlier animal experiment, see our ADA rat-study review. The animal and human studies address different questions.
Is Eloralintide approved for medical use?
No. Eloralintide remains an investigational therapy and continues to be evaluated through clinical research. Like all investigational compounds, its safety and efficacy must continue to be assessed through larger clinical studies before any regulatory decisions can be made.
What stage of clinical development is Eloralintide currently in?
Eloralintide is currently being evaluated through ongoing clinical development. Lilly continues to study the compound both as a standalone therapy and as part of broader research programs exploring combination approaches for obesity and metabolic disease.
Could Eloralintide eventually be combined with other obesity therapies?
One of the most interesting aspects of current research is the exploration of combination biology. Scientists are increasingly investigating whether therapies that target different hormonal pathways may provide complementary effects when used together.
The ongoing interest surrounding Eloralintide reflects this broader scientific trend, although additional clinical research will determine how these strategies evolve over time.
Why is Lilly investing in multiple obesity therapies instead of a single drug?
Obesity is a complex disease involving numerous interconnected hormonal systems that regulate appetite, metabolism, energy expenditure, and body weight. Rather than relying on a single biological pathway, many pharmaceutical companies are investigating multiple therapeutic approaches simultaneously.
Lilly’s metabolic research pipeline includes incretin-based therapies, triple agonists, selective amylin receptor agonists, and combination research programs, reflecting a broader strategy aimed at understanding how complementary mechanisms may improve long-term treatment outcomes.
Where can I follow future Eloralintide updates?
As additional conference presentations, clinical publications, and scientific updates become available, this article will be updated to reflect the latest developments. Our goal is to provide an accurate, science-focused resource that follows Eloralintide’s clinical progress and the broader evolution of next-generation obesity therapeutics.
2 thoughts on “Eloralintide + Tirzepatide: Why the Obesity Research Community Is Suddenly Paying Close Attention”
Excellent info! Looking forward to seeing what the outcomes are in combination with Triz. However, my major interests are in the beyond weight loss alone section. G.I. tolerability and a simple maintenance program are going to be huge, avoiding any lien muscle mass wasting. And of course, very interested in any effects on any other system in the body. Thanks for your work🙏
Thanks Teresa, really appreciate the kind words 🙏
I’m with you on that. The “beyond weight loss” side of this is where things get really interesting. GI tolerability, maintenance, lean mass, and how these compounds may affect other systems are all big questions researchers will be watching closely. The lean mass piece especially matters. It’s not just about total weight change, but what kind of weight is changing and how that looks over time in research settings. Still a lot to learn with eloralintide and tirzepatide together, but that’s exactly why this area is getting so much attention. Thanks again for reading and for the thoughtful comment!